How to Decode Your Pulmonary Function Test Results: A Step-by-Step Guide
Pulmonary function tests (PFTs) are the diagnostic cornerstone for assessing lung health, yet many patients leave the clinic with a stack of numbers and little clarity on what they mean. The ability to read pulmonary function test results is not just about identifying normal ranges—it’s about recognizing patterns, understanding deviations, and correlating findings with symptoms. A forced expiratory volume (FEV1) of 70% predicted may sound technical, but it could signal early obstructive disease if paired with a low FEV1/FVC ratio. Misinterpretation can lead to delayed treatment or unnecessary anxiety; conversely, accurate self-awareness empowers patients to advocate for their care.
The process begins with the test itself: a series of breaths into a mouthpiece connected to a spirometer, measuring airflow, lung volumes, and gas exchange. But the real work happens afterward—when clinicians (or informed patients) translate those curves and values into actionable insights. For example, a restrictive pattern might show reduced total lung capacity (TLC) with preserved ratios, while obstructive diseases like COPD or asthma typically reveal airflow limitation. The challenge lies in distinguishing between these patterns, especially in mixed presentations, where both obstructive and restrictive elements coexist.
What separates a routine check from a critical diagnosis is often the nuance in how to read pulmonary function test results effectively. A single abnormal value rarely tells the full story; it’s the interplay between metrics—such as residual volume (RV), diffusion capacity (DLCO), and response to bronchodilators—that paints a clearer picture. This guide dissects the methodology behind PFT interpretation, from foundational principles to advanced diagnostic clues, ensuring you can navigate your results with confidence.

The Complete Overview of Reading Pulmonary Function Test Results
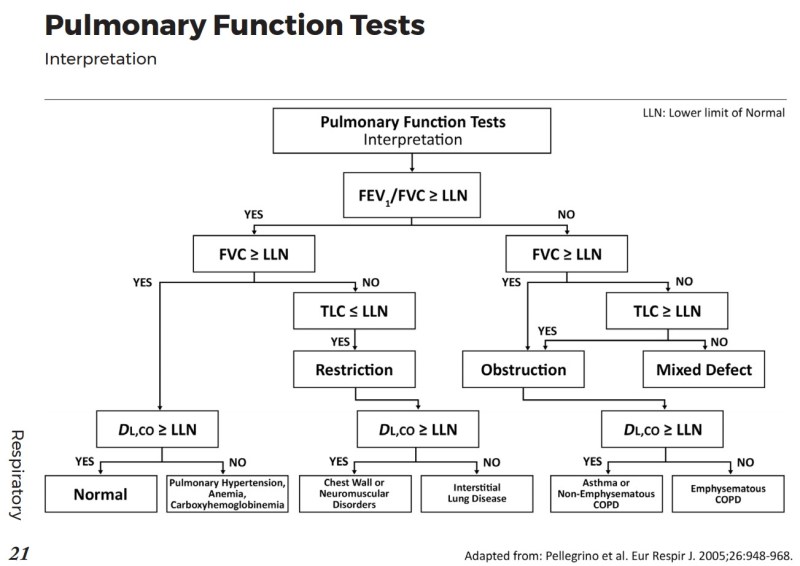
Pulmonary function tests are standardized evaluations designed to quantify lung mechanics, gas exchange efficiency, and structural integrity. The most common test, spirometry, measures how much air you can exhale forcefully (FEV1) and the total volume exhaled over six seconds (FVC). When reading pulmonary function test results, these values are compared to predicted norms based on age, sex, height, and ethnicity, yielding percentages that indicate whether your lungs are functioning optimally. For instance, an FEV1 of 85% predicted suggests near-normal airflow, while a value below 50% may warrant further investigation for severe obstruction or restriction.Beyond spirometry, extended PFTs include lung volume measurements (TLC, RV) and diffusion capacity tests (DLCO), which assess how efficiently oxygen transfers across the alveolar membrane. These additional tests help differentiate between obstructive diseases (e.g., COPD, asthma) and restrictive conditions (e.g., pulmonary fibrosis, sarcoidosis). The key to understanding how to read pulmonary function test results lies in recognizing these distinct patterns: obstructive diseases typically show reduced FEV1 with a low FEV1/FVC ratio (<0.7), whereas restrictive diseases may present with low TLC and normal or high ratios. Mastering these distinctions is critical for accurate diagnosis and treatment planning.
Historical Background and Evolution
The roots of pulmonary function testing trace back to the early 20th century, when physicians sought objective methods to quantify lung capacity beyond clinical examination. Early spirometers, developed in the 1920s, relied on water-filled drums to measure exhaled volumes—a far cry from today’s digital precision. The field advanced significantly during World War II, as military physicians used PFTs to screen recruits for respiratory fitness, revealing the prevalence of undiagnosed lung conditions. By the 1960s, standardized reference equations emerged, allowing clinicians to compare individual results to population norms, a cornerstone of modern how to read pulmonary function test results methodology.Technological innovations in the 1980s and 1990s revolutionized PFTs, introducing computer-driven analysis and body plethysmography to measure lung volumes without reliance on patient cooperation. These advancements enabled more accurate diagnoses of complex conditions, such as mixed obstructive-restrictive patterns. Today, PFTs are integrated with imaging (CT scans) and blood gas analysis, creating a multidisciplinary approach to respiratory assessment. The evolution reflects a broader shift from reactive to predictive medicine, where interpreting pulmonary function test results now includes monitoring disease progression and evaluating treatment efficacy in real time.
Core Mechanisms: How It Works
At its core, spirometry evaluates two primary functions: airflow limitation and lung volume dynamics. During the test, patients inhale deeply and exhale forcefully into a spirometer, generating a flow-volume loop that plots exhaled airflow against time. The FEV1 measures the volume exhaled in the first second, while the FVC captures the total exhaled volume over six seconds. When reading pulmonary function test results, the FEV1/FVC ratio is critical: a ratio below 0.7 suggests airflow obstruction, whereas a normal ratio with low FEV1 may indicate restriction or neuromuscular weakness. This ratio is particularly useful in distinguishing between asthma (variable obstruction) and COPD (fixed obstruction).Table of Contents
- The Complete Overview of Reading Pulmonary Function Test Results
- Historical Background and Evolution
- Core Mechanisms: How It Works
- Key Benefits and Crucial Impact
- Major Advantages
- Comparative Analysis
- Future Trends and Innovations
- Conclusion
- Comprehensive FAQs
- Q: What does an FEV1/FVC ratio below 0.7 indicate?
- Q: Can pulmonary function tests diagnose asthma?
- Q: What does a low DLCO mean?
- Q: How often should I repeat pulmonary function tests?
- Q: What if my PFT results are normal but I still have symptoms?
- Q: Are there any limitations to pulmonary function testing?
Lung volume tests, such as body plethysmography, assess total lung capacity (TLC) and residual volume (RV) by creating a sealed chamber where pressure changes reflect lung volume. Diffusion capacity tests (DLCO) measure how quickly oxygen passes from alveoli to blood, revealing potential issues with alveolar surface area or capillary blood flow. When combined, these metrics provide a comprehensive profile. For example, a low DLCO with normal spirometry might indicate interstitial lung disease, while a high RV/TLC ratio often points to air trapping in obstructive diseases. Understanding these mechanisms is essential for accurately interpreting pulmonary function test results in clinical practice.
Key Benefits and Crucial Impact
The primary advantage of pulmonary function testing lies in its ability to quantify respiratory impairment objectively, bridging the gap between subjective symptoms (e.g., shortness of breath) and measurable pathology. For patients with chronic conditions like COPD or asthma, PFTs serve as a biomarker for disease severity, guiding treatment decisions such as inhaler therapy or oxygen supplementation. Clinicians rely on these tests to monitor progression, assess response to interventions, and determine eligibility for advanced therapies, such as lung transplantation. The impact extends beyond diagnosis: reading pulmonary function test results can reveal early signs of occupational lung diseases or environmental exposures, enabling preventive measures before irreversible damage occurs.PFTs also play a pivotal role in research and public health, where large-scale studies use spirometry data to track population-level trends in respiratory health. For instance, declines in FEV1 over decades have highlighted the global burden of smoking and air pollution. In clinical trials, PFTs are endpoints for evaluating new drugs, with changes in FEV1 or DLCO serving as surrogates for treatment efficacy. The versatility of these tests—from bedside diagnostics to global epidemiology—underscores their indispensable role in modern medicine.
"Pulmonary function tests are the Rosetta Stone of respiratory medicine: they translate clinical symptoms into a language of numbers that can be measured, compared, and acted upon."
— Dr. John R. Balmes, Professor of Medicine, University of California, San Francisco
Major Advantages
- Early Detection: PFTs can identify airflow obstruction or restriction before symptoms become severe, allowing for timely intervention in conditions like COPD or pulmonary fibrosis.
- Disease Differentiation: The combination of FEV1/FVC ratios, lung volumes, and DLCO helps distinguish between obstructive (e.g., asthma, COPD) and restrictive (e.g., sarcoidosis, ILD) patterns, guiding targeted therapy.
- Treatment Monitoring: Serial PFTs track disease progression or improvement, such as FEV1 changes after bronchodilator use or following pulmonary rehabilitation.
- Pre-Surgical Assessment: Tests like DLCO are critical for evaluating candidates for lung resection or transplantation, predicting postoperative lung function.
- Occupational and Environmental Health: PFTs screen for work-related lung diseases (e.g., asbestosis, silicosis) and assess exposure risks in high-risk professions.

Comparative Analysis
| Obstructive Disease (COPD/Asthma) | Restrictive Disease (Pulmonary Fibrosis/Sarcoidosis) |
|---|---|
|
|
| Mixed Pattern (e.g., Combined COPD + ILD) | Normal Findings |
|
|
Future Trends and Innovations
The next frontier in pulmonary function testing lies in integrating PFTs with wearable technology and artificial intelligence. Portable spirometers, such as those used in home monitoring, are already enabling remote tracking of lung function, particularly for patients with chronic diseases. AI algorithms are being developed to analyze flow-volume loops and detect subtle patterns that may escape human interpretation, potentially identifying early-stage diseases like idiopathic pulmonary fibrosis. Additionally, advances in imaging-PFT fusion—combining spirometry with CT scans—are creating dynamic models of lung function, allowing for personalized risk stratification.Another emerging trend is the use of biomarkers in conjunction with PFTs. For example, exhaled nitric oxide (eNO) levels can differentiate between eosinophilic asthma and other obstructive diseases, while blood tests for surfactant proteins (e.g., KL-6) may complement DLCO in diagnosing interstitial lung disease. These innovations are poised to make reading pulmonary function test results more precise, accessible, and actionable, shifting from reactive to predictive respiratory care.
Conclusion
Pulmonary function tests are more than diagnostic tools—they are gateways to understanding the functional capacity of the lungs and the underlying mechanisms of respiratory disease. Whether you’re a clinician interpreting spirometry curves or a patient navigating your own test results, the ability to read pulmonary function test results accurately is paramount. The interplay between airflow limitation, lung volumes, and gas exchange provides a roadmap for diagnosis, treatment, and monitoring, but it requires a nuanced approach to avoid misinterpretation.As technology evolves, the future of PFTs will likely emphasize personalized medicine, where data from spirometry, imaging, and biomarkers converge to create tailored treatment plans. For now, the foundational principles remain unchanged: understanding the patterns, recognizing the deviations, and translating numbers into meaningful clinical insights. In an era where respiratory diseases continue to rise, mastering the art of interpreting pulmonary function test results is not just a skill—it’s a necessity.
Comprehensive FAQs
Q: What does an FEV1/FVC ratio below 0.7 indicate?
A: An FEV1/FVC ratio below 0.7 is a hallmark of airflow obstruction, commonly seen in obstructive lung diseases like COPD or asthma. This ratio suggests that less than 70% of the total exhaled volume (FVC) is expelled in the first second (FEV1), indicating resistance in the airways. However, clinical correlation is essential, as other conditions (e.g., neuromuscular disorders) can also affect this ratio.
Q: Can pulmonary function tests diagnose asthma?
A: While PFTs cannot definitively diagnose asthma on their own, they play a crucial role in the diagnostic process. A reversible airflow obstruction (improvement in FEV1 ≥ 12% and ≥ 200 mL after bronchodilator use) strongly suggests asthma. However, diagnosis often requires a combination of PFTs, symptom history, and possibly methacholine challenge testing or peak flow monitoring.
Q: What does a low DLCO mean?
A: A low diffusion capacity of the lung for carbon monoxide (DLCO) indicates impaired gas exchange, often due to reduced alveolar surface area (e.g., pulmonary fibrosis) or decreased capillary blood flow (e.g., pulmonary hypertension). It can also occur in conditions like emphysema, where alveolar destruction reduces diffusion capacity. Clinical context is key, as DLCO may be normal in early obstructive disease.
Q: How often should I repeat pulmonary function tests?
A: The frequency depends on the clinical scenario. For stable chronic diseases (e.g., COPD), annual or biennial testing may suffice to monitor progression. In acute settings (e.g., post-bronchodilator response), tests may be repeated within hours. Patients with suspected occupational lung diseases or those undergoing treatment for interstitial lung disease may require more frequent assessments, as guided by their healthcare provider.
Q: What if my PFT results are normal but I still have symptoms?
A: Normal PFTs do not rule out respiratory conditions, especially if symptoms are mild or intermittent. Other causes—such as deconditioning, anxiety, cardiac-related dyspnea, or early-stage diseases—may not yet manifest on spirometry. Further evaluation, including imaging (chest X-ray/CT), blood tests, or exercise testing, may be necessary to identify alternative explanations for your symptoms.
Q: Are there any limitations to pulmonary function testing?
A: Yes. PFTs rely on patient effort and cooperation, which can be challenging for children, elderly patients, or those with cognitive impairments. Obesity, recent surgery, or certain medical conditions (e.g., pneumothorax risk) may also limit test accuracy. Additionally, PFTs assess lung mechanics but do not directly evaluate conditions like pleural disease or central airway obstruction without additional imaging or tests.
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Bevvy.